










Living with a lung disease can make everyday activities like walking, climbing stairs, or doing household work difficult. You may feel breathless, tired, or weak even after doing simple tasks. Pulmonary rehabilitation helps people with lung diseases manage these challenges and improve their quality of life. It includes breathing exercises, physical activities, nutritional guidance, and support from healthcare professionals. These activities help improve lung function, build strength, and make breathing easier. Pulmonary rehabilitation can benefit people with conditions like COPD, asthma, and other long-term lung diseases. It helps patients feel more confident and manage their daily activities better.
What Is Pulmonary Rehabilitation?
Pulmonary rehabilitation is a supervised programme of graded exercise, breathing retraining, education and practical support, and it is built for those patients whose lungs no longer sustain an ordinary life.
It treats the consequences rather than the disease itself, because the medication acts on the lungs while pulmonary rehabilitation acts on the wasted muscle, the lost stamina and the fear that medication cannot reach.
Sessions are held two or three times a week across several weeks, and the intensity of each one of them is set by the condition the patient presents with on that morning.
Why Is Pulmonary Rehabilitation Important for Lung Diseases?
A cycle sits under most chronic lung disease. It runs in roughly the following way. Breathlessness makes movement unpleasant, so the patient moves less, and then the muscle wastes, and the wasted muscle needs more oxygen for the same piece of work. Good pulmonary rehabilitation manages the pain and other lung problems.
Managing breathlessness. Pursed lip and diaphragmatic breathing supply a patient with something to do during an episode other than panic, and the panic itself is what extends four difficult minutes out into fifteen difficult minutes.
Improving exercise tolerance. Graded training restores the stamina that a year of declining invitations and of avoiding the staircase will have quietly taken out of a patient.
Building strength for everyday activities. The aim here is not fitness. It is the staircase at home. It is the bathroom at night and the walk out to the gate.
Supporting confidence and quality of life. Fear of the breathlessness keeps a patient indoors just as surely as the breathlessness itself does, and supervised practice is the thing that settles it.
At Antara a PM&R specialist directs the whole programme and in house physiotherapists deliver it, so the sessions proceed on schedule rather than lapsing in those weeks when a visiting therapist is unavailable. Nursing staff and caregivers are present overnight, and the rooms are fitted with an in built oxygen pipeline and with emergency call buttons, which matter a great deal when respiratory reserve is thin. Insurance claim support takes on the paperwork as well, which spares a family one further burden during what is usually quite a long admission.
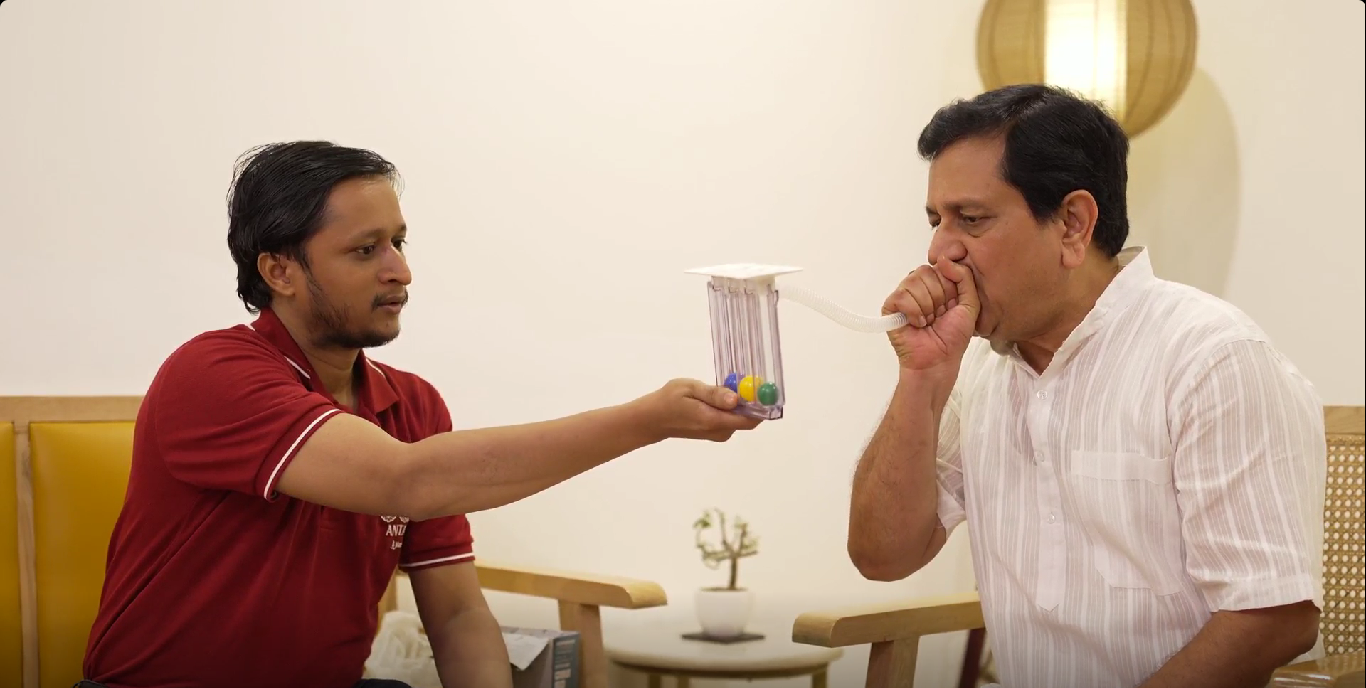
Which Lung Conditions Can Benefit From Pulmonary Rehabilitation?
Chronic obstructive pulmonary disease. Pulmonary rehabilitation is recommended for people with *chronic obstructive pulmonary disease* (COPD), interstitial lung disease, pulmonary fibrosis, asthma, and other chronic respiratory conditions
Interstitial lung disease, pulmonary fibrosis included. The benefit is established here as well, though the aims are set around holding on to whatever function still remains, since the disease keeps advancing.
Other chronic respiratory conditions are taken on individual clinical assessment. Bronchiectasis, asthma that has begun to govern a patient’s day, recovery after a pneumonia that needed a long admission, and the breathlessness that persists after a viral illness are each of them judged separately.
The diagnosis itself rarely decides the matter, because what does decide it is whether the breathlessness has begun dictating how a patient is able to spend his day.
What Does a Pulmonary Rehabilitation Programme Include?
Supervised exercise and mobility training. This is the bulk of the programme, and walking endurance, cycling and leg strengthening come first, because the large leg muscles generate most of the breathlessness that a patient feels during ordinary movement. Upper limb work follows after that, since reaching up to a shelf proves harder than most families expect, and nothing is ever advanced beyond what a patient can tolerate.
Breathing techniques. Taught, then rehearsed. Rehearsed until they have become entirely automatic. Pursed lip breathing slows the exhalation and prevents the small airway collapse that traps the air within the chest. Diaphragmatic breathing moves the effort away from the neck and from the shoulders, which tire rapidly, and patients also learn the positions of ease that will carry them through an episode.
https://pmc.ncbi.nlm.nih.gov/articles/PMC7515680
Education on managing symptoms. Inhaler technique is addressed first, since a large proportion of patients have been using it wrongly for years unchecked, and recognising a flare early and knowing when to telephone will both follow after that.
Nutrition and energy conservation. Many patients at this stage are underweight, since laboured breathing burns calories both day and night, and pacing then teaches a patient how to plan a day he is able to complete.
Psychological and self management support. This addresses the anxiety that accompanies the breathlessness, along with the flatness that follows a year of diminishing activity.
Who Should Consider Pulmonary Rehabilitation, and When?
A good deal sooner than most of the referrals are actually made.
Consider it once the breathlessness restricts an ordinary day, after repeated admissions, after any severe flare, or once a patient has stopped leaving the house at all. Delay it until he is housebound and the work becomes a good deal harder, while the gains at the end become smaller.
FAQs
Does pulmonary rehabilitation improve lung function? Ordinarily not. The spirometry readings remain broadly unchanged, while the exercise capacity, the breathlessness and the quality of life all improve, which is the distinction that families find most confusing.
How long does pulmonary rehabilitation take? Six to twelve weeks under supervision, and then the maintenance exercises at home, which hold on to the gains for precisely as long as a patient keeps doing them.
Can pulmonary rehabilitation help with breathlessness? Yes. Patients tend to notice this one first, frequently within a fortnight of commencing the programme.
Conclusion
Chronic lung disease takes the ordinary activities away one at a time, and the medication alone gives very few of them back.
When a patient stops climbing his own staircase at home, that is the point at which a doctor ought to be asked about pulmonary rehabilitation. This article is for general information and is not a substitute for medical advice.